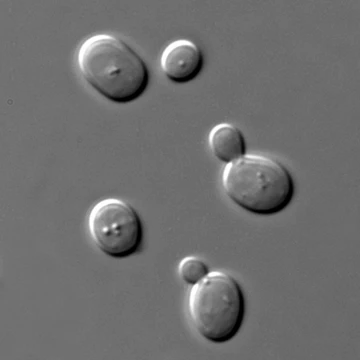
Candida dubliniensis
Opportunistic yeast closely related to Candida albicans, often misidentified.

Candida dubliniensis is a fungus that can cause opportunistic infections. It belongs to the genus *Candida* and is a close relative of *Candida albicans*, though DNA fingerprinting places it in its own distinct group. This pathogen was first found in AIDS patients, but it can also turn up in people with healthy immune systems. The mouth is the most common site for isolation, though it has been found elsewhere in the body.
The species is found worldwide and was officially described as separate in 1995. Before that, it was often mistaken for *C. albicans* because the two share many traits. One way to tell them apart in the lab is by temperature: most *C. albicans* strains grow at 42 °C, while most *C. dubliniensis* do not. They also differ in the conditions that trigger chlamydospore formation, even though they look very similar otherwise.
At Memorial Sloan-Kettering Cancer Center, researchers looked at 974 germ-tube positive yeasts and found 22 isolates (2.3%) from 16 patients were *C. dubliniensis*. All those patients had weakened immune systems due to cancer or AIDS, and the samples came from various body sites. Another study found the fungus in the mouths of 18% of diabetic patients who use insulin.
Regarding treatment, one study tested 20 isolates and found all were susceptible to itraconazole, ketoconazole, and amphotericin B. For fluconazole, 16 out of 20 isolates were sensitive, but four were resistant. It is thought that *C. dubliniensis* can quickly develop resistance to fluconazole, especially in patients on long-term therapy.
Quick Facts
- Genus
- Candida
- Species
- dubliniensis
Facts from the source article.
Lore & Background
Candida dubliniensis was described as a separate species in 1995. Retrospective studies have shown that previously it had been commonly identified as Candida albicans, with which it shares many characteristics. One test for distinguishing C. dubliniensis from C. albicans is laboratory culture at 42 °C: most C. albicans strains grow at this temperature, whereas most C. dubliniensis isolates do not. There are also significant differences in the conditions that lead to the formation of chlamydospores between the two species, although they are otherwise phenotypically very similar.
The Memorial Sloan-Kettering Cancer Center conducted several studies. In 974 germ-tube positive yeasts, 22 isolates (2.3%) from 16 patients were C. dubliniensis. All individuals were immunologically compromised with either malignancy or AIDS, and the isolates came from a variety of different sites. C. dubliniensis was also isolated from the mouths of 18% of patients with diabetes and who use insulin.
Regarding antifungal susceptibility, in one study all 20 C. dubliniensis isolates tested were susceptible to itraconazole, ketoconazole and amphotericin B. Many isolates are sensitive to fluconazole, but in one study four of twenty isolates were resistant. It has been hypothesized that C. dubliniensis possesses the ability to rapidly develop resistance to fluconazole, especially in patients on long-term therapy.
Reader's Guide
Candida dubliniensis is notable as an opportunistic pathogen that was historically misidentified as Candida albicans due to their close phenotypic similarity. Its recognition as a distinct species in 1995 clarified a source of infection in immunocompromised populations, particularly those with AIDS or malignancy, as shown by the Memorial Sloan-Kettering Cancer Center studies where 2.3% of germ-tube positive yeasts were this species. The organism is cosmopolitan and also found in immunocompetent individuals, though most commonly in oral cavities. Its significance lies in its differential diagnosis from C. albicans, which requires specific laboratory tests such as growth at 42 °C or chlamydospore formation conditions. Antifungal susceptibility patterns are generally favorable, with all tested isolates susceptible to itraconazole, ketoconazole, and amphotericin B. However, fluconazole resistance occurs in a minority of isolates, and the species may rapidly develop resistance during long-term therapy, posing a clinical challenge. The article does not provide further details on treatment outcomes or broader epidemiological impact beyond these findings.
Did You Know?
- It is most commonly isolated from oral cavities.
- In one study, 4 of 20 isolates were resistant to fluconazole.
More in Yeasts 1-24
Spotted an error? Know more?
Reader corrections go straight into our review queue. Suggest an edit · How this site is sourced