Cogan syndrome
Rare disorder causing eye and ear inflammation, potentially leading to deafness or blindness.

Cogan syndrome is a rare condition marked by repeated inflammation of the cornea—the clear front part of the eye—along with symptoms like fever, fatigue, weight loss, vertigo, tinnitus, and hearing loss. Without treatment, it can result in deafness or blindness. The classic form was first identified by D. G. Cogan in 1945. This rheumatic disease causes inflammation in the eyes and ears, leading to vision problems, hearing loss, and dizziness. In about 15% of cases, inflammation of blood vessels (vasculitis) can spread to other organs, potentially causing major damage or, rarely, death. It most often appears in a person’s 20s or 30s. The exact cause is unknown, but it is thought to be an autoimmune disorder where the immune system mistakenly attacks eye and ear tissue. Some patients have autoantibodies in their blood that target inner ear tissue in lab tests. Infection with *Chlamydia pneumoniae*—a common cause of mild pneumonia—has been found in some patients before the syndrome develops, suggesting the infection might trigger the autoimmune response, though most people infected with this bacterium never develop Cogan syndrome. Diagnosis is tricky. Blood tests may show abnormal white blood cell counts, high erythrocyte sedimentation rate, elevated C-reactive protein, high platelet levels, or low red blood cell counts, but none reliably confirm the disease. A slit-lamp eye exam is essential. High-resolution MRI and tests for antibodies against inner ear antigens may also help. The syndrome can occur in children, where it is especially hard to recognize. For severe cases, oral corticosteroids are used to reduce inflammation. If high doses are needed or the disease doesn’t respond, other immunosuppressive drugs like methotrexate, cyclophosphamide, cyclosporine, or azathioprine may be prescribed, sometimes in combination. If blood vessel damage in the ear occurs, a cochlear implant can help restore some hearing. Cinnarizine is mainly used to treat nausea and vomiting associated with motion sickness, vertigo, Ménière's disease, or Cogan syndrome.
- Field
- Rheumatic disease
- Known for
- Inflammation of the eyes and ears, potential deafness or blindness
- First described by
- D. G. Cogan
- Year first described
- 1945
- Typical age of onset
- 20s or 30s
Lore & Background
Cogan syndrome is a rare, rheumatic disease characterized by inflammation of the ears and eyes. It can lead to vision difficulty, hearing loss, and dizziness. The condition may also be associated with blood-vessel inflammation (vasculitis) in other areas of the body, which can cause major organ damage in 15% of those affected or, in a small number of cases, even death. It most commonly occurs in a person's 20s or 30s. The cause is not known, but one theory is that it is an autoimmune disorder in which the body's immune system mistakenly attacks tissue in the eye and ear. The inflammation in the eye and ear is thought to be due to the patient's own immune system producing antibodies that attack the inner ear and eye tissue. Autoantibodies can be demonstrated in the blood of some patients, and these antibodies have been shown to attack inner ear tissue in laboratory studies. Infection with the bacteria Chlamydia pneumoniae has been demonstrated in some patients prior to the development of Cogan syndrome, leading some researchers to hypothesize that the autoimmune disease may be initiated by the infection. However, the vast majority of patients infected with C. pneumoniae do not develop Cogan syndrome.
Reader's Guide
Cogan syndrome is significant as a rare but potentially devastating disorder that can cause both deafness and blindness if untreated. Its recognition is critical, as early treatment with corticosteroids or immunosuppressive medications may reduce inflammation and prevent permanent damage. The disease was first described by ophthalmologist D. G. Cogan in 1945, and an atypical form, known as Logan Syndrome, was first described in 1963. Diagnosis remains challenging, as no single test is reliable; a slit-lamp examination is essential, and high-resolution MRI and antibodies to inner ear antigens may be helpful. The condition can occur in children, where it is particularly difficult to recognize. Treatment options include oral corticosteroids, immunosuppressive drugs such as methotrexate, cyclophosphamide, cyclosporine, or azathioprine, and in some cases cochlear implantation for hearing restoration. Cinnarizine is used to treat nausea, vomiting, vertigo, and hearing loss associated with the syndrome. The cause is uncertain, but an autoimmune mechanism is suspected, possibly triggered by infection with Chlamydia pneumoniae in some patients.
Did You Know?
- Cogan syndrome can lead to deafness or blindness if untreated.
- The classic form was first described by D. G. Cogan in 1945.
- Infection with Chlamydia pneumoniae has been found in some patients before developing Cogan syndrome.
Classification Within the Chapel Hill Framework
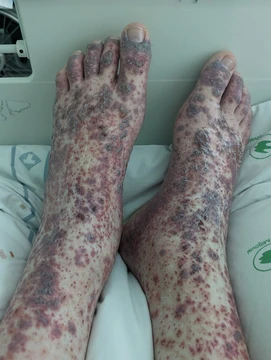
Cogan syndrome occupies a distinct niche within the taxonomy of vasculitis, a family of disorders defined by inflammatory destruction of blood vessels. Under the nomenclature established at the 2012 Chapel Hill Consensus Conference, primary systemic vasculitis is divided into four subcategories based on the size of vessels predominantly involved: large-vessel, medium-vessel, small-vessel, and variable-vessel vasculitis. Cogan syndrome falls squarely into the last of these groups, the variable-vessel category, alongside Behcet's disease. This placement sets it apart from conditions like Takayasu arteritis or giant cell arteritis, which target the aorta and its major branches, or from polyarteritis nodosa and Kawasaki disease, which center on medium-sized arteries supplying the viscera. The variable designation signals that no single vessel caliber or type holds dominance, a defining feature that distinguishes Cogan syndrome from the more anatomically constrained forms of the disease family.
The Variable Vessel Pattern
What makes Cogan syndrome pathologically distinctive is the breadth of vascular territory it can compromise. In variable-vessel vasculitis, the inflammatory process is not tethered to one particular vessel size or type. Arteries, veins, and capillaries may all be targeted, and the damage can span small, medium, and large calibers without any one group being predominantly affected. This stands in sharp contrast to large-vessel vasculitis, where the aorta and its principal branches bear the brunt, or to small-vessel forms where immune complexes or antineutrophil cytoplasmic antibodies drive necrotizing injury in the microvasculature. At the cellular level, the destruction in vasculitis is driven primarily by leukocyte migration into the vessel wall and the resultant tissue damage. Both arterial and venous structures are susceptible, and in some classifications, even lymphatic vessel inflammation is grouped under the broader vasculitis umbrella. For Cogan syndrome, this means the inflammatory assault can theoretically reach any vascular compartment, making the clinical picture inherently more heterogeneous than in size-restricted vasculitides.
Etiologic Landscape and Immune Drivers
The causes of vasculitis span a wide spectrum, and Cogan syndrome, as a primary systemic variable-vessel condition, sits within a landscape where autoimmune dysregulation plays a particularly prominent role. Among the various etiologies—ranging from infections to simple vascular thrombosis to drug exposure—autoimmune mechanisms, characterized by dysregulated immune responses that produce specific pathophysiologic signs, are noted as more prevalent in the vasculitis family. Infections, while usually a component of broader tissue damage, can also trigger vasculitic syndromes through immune-mediated secondary events. Even simple thrombosis, when it progresses through thrombus organization, can occasionally give rise to a more chronic vasculitic picture. Secondary vasculitis, triggered by underlying conditions such as rheumatoid arthritis, cancer, or specific infections including hepatitis B and C, HIV, infective endocarditis, and tuberculosis, represents another layer of the disease ecology. Cogan syndrome, classified as a primary systemic form, is distinguished from these secondary triggers, yet the broader immune-mediated mechanisms that drive vessel destruction remain a shared thread across the entire vasculitis spectrum.
Diagnostic Pathways and Tissue Evidence
Establishing a definitive diagnosis of vasculitis, including Cogan syndrome, ultimately hinges on tissue-level evidence. Laboratory workups in active disease typically reveal markers of systemic inflammation—elevated erythrocyte sedimentation rate, raised C-reactive protein, anemia, increased white blood cell counts, and eosinophilia—while some patients may show elevated antineutrophil cytoplasmic antibody levels or hematuria. Organ functional tests can be abnormal depending on the degree of involvement, and imaging such as brain SPECT may reveal decreased cerebral blood flow. However, the gold standard remains biopsy of the affected organ or tissue, whether that is skin, sinuses, lung, nerve, brain, or kidney, because the biopsy directly elucidates the pattern of blood vessel inflammation. Certain vasculitides display leukocytoclasis, where nuclear debris from infiltrating neutrophils causes vascular damage, often presenting as palpable purpura. An angiogram, an x-ray-based visualization of blood vessels, serves as an alternative diagnostic tool, capable of demonstrating characteristic inflammatory patterns in affected vessels. For a variable-vessel condition like Cogan syndrome, the absence of a single predominant vessel type means the diagnostic workup must remain broad in scope.
Frequently Asked Questions
Who is Cogan syndrome?
Cogan syndrome is a rare rheumatic condition named after D. G. Cogan, who first described the classic form in 1945. It primarily targets the eyes and ears, causing recurring corneal inflammation alongside vestibular and auditory symptoms.
What is Cogan syndrome known for?
It attacks the cornea with repeated bouts of inflammation and simultaneously disrupts the inner ear, producing vertigo, tinnitus, and progressive hearing loss. Patients also commonly experience fever, fatigue, and unexplained weight loss during active episodes.
Why is Cogan syndrome important?
It serves as a key example of how a rheumatic disorder can simultaneously devastate two sensory systems and, in a subset of patients, escalate into a systemic vasculitis. Its rarity and the severity of its untreated outcomes make it a critical diagnosis for rheumatologists and ophthalmologists to recognize early.
When does Cogan syndrome typically debut?
The condition most often presents in a person's twenties or thirties. It is considered rare, and early identification is crucial because the window to prevent permanent vision or hearing loss is limited.
More in Vasculitis 1-24
Spotted an error? Know more?
Reader corrections go straight into our review queue. Suggest an edit · How this site is sourced