
Burn center
Hospital specializing in treatment of severe burns.

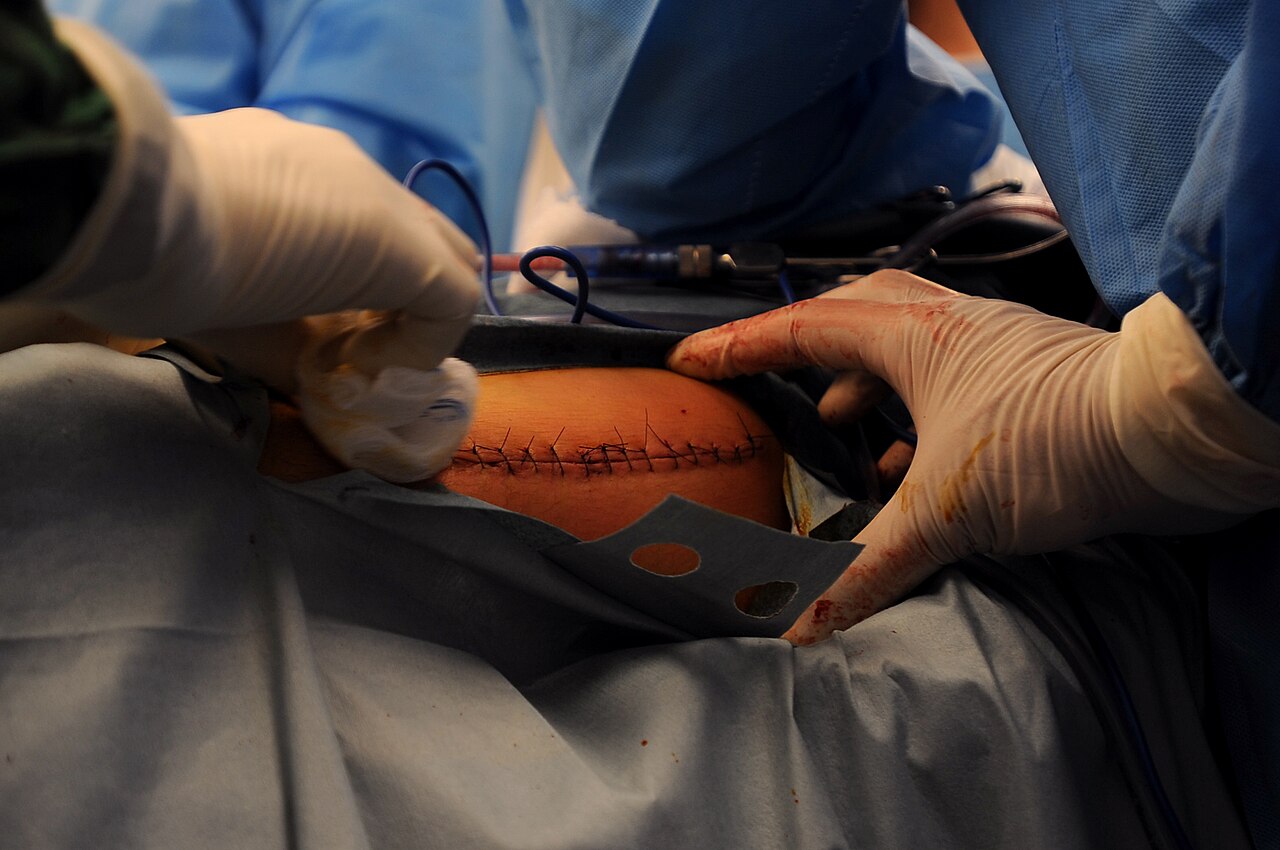
Burn & Trauma Research Center · CC BY-SA 3.0
A burn center—also called a burn ward, burn unit, or burns unit—is a hospital department dedicated to treating burn injuries. These facilities primarily handle the care and recovery of patients with serious burns.
Whether a patient is referred to a burn center after initial stabilization depends on several factors. The victim's age matters: burns to infants, toddlers, and people over 65 are generally more serious, especially if the face, head, respiratory system, chest, abdomen, groin, or limbs are affected. Patients outside these age groups may also be at higher risk if they were already ill, injured, or had a weakened immune system. The total body surface area burned (assessed using the rule of nines) is another key factor. Delayed or incorrect treatment can worsen outcomes. The depth of the burn also plays a role—second, third, and fourth-degree burns are more severe the larger and deeper they are. The burn's source (chemical, scald, fire, or radiation) requires specific treatment adjustments. Finally, if skin grafting is not possible or if vital organs are damaged, the case becomes more critical.
Managing severely burned patients requires a team approach. The burn care team typically includes an intensivist, burn nurse, plastic surgeon, chest physician, general surgeon, anesthesiologist, respiratory therapist, pediatrician, technicians, microbiologist, psychiatrist, nutritionist, physiotherapist, and social worker. Early removal of burned tissue and immediate wound coverage can improve survival rates in major burn cases.
Lists of burn centers exist for Australia, Canada, Bahrain, the United Kingdom, and the United States.
- Field
- Medicine (burn treatment)
- Known for
- Specialized treatment of severe burns
- Team members
- Intensivist, burn nurse, plastic surgeon, chest physician, general surgeon, anesthesiologist, respiratory therapist, pediatrician, technicians, microbiologist, psychiatrist, nutritionist, physiotherap
Lore & Background
A burn center requires a team approach for the management of critically burned patients. The burns management team typically consists of an intensivist, burn nurse, plastic surgeon, chest physician, general surgeon, anesthesiologist, respiratory therapist, pediatrician, technicians, microbiologist, psychiatrist, nutritionist, physiotherapist, and social worker. Early burn wound excision and immediate wound cover can improve the chances of survival in major burn cases.
Reader's Guide
The severity of a burn, and whether a referral will be made after the patient is treated and stabilized, depends on many factors. These include the age of the victim, with burns to infants, toddlers, and those over age 65 generally being more serious, particularly if the face, head, respiratory system, chest, abdomen, groin, or extremities are burned. Those not in these age groups can be more affected if they are already ill, injured, or immunocompromised. Other factors include the total body surface area burned (assessed by the rule of nines), whether proper treatment and referrals are delayed or wrong treatments are given, the degree of burn (2nd, 3rd, or 4th degree), the source of the burn (chemical, scald, fire, or radiation), and whether skin grafting is not feasible or important organs are harmed. Burn centers exist in various countries, including Australia, Canada, Bahrain, the United Kingdom, and the United States.
Did You Know?
- Burn centers are often used for the treatment and recovery of patients with more severe burns.
- The severity of a burn depends on factors including the victim's age, total body surface area burned, and burn degree.
- A burn center's team typically includes an intensivist, burn nurse, plastic surgeon, and social worker.
- Early burn wound excision and immediate wound cover can improve survival chances in major burn cases.
How Different Radiation Types Injure the Body
Radiation burns represent a broad category of tissue injury, spanning everything from the familiar redness of a sunburn to deep internal damage from ionizing particles. The four radiation types of greatest medical concern are thermal radiation, radio frequency energy, ultraviolet light, and ionizing radiation. Each interacts with biological tissue in distinct ways. Ultraviolet exposure produces the most common radiation burn—sunburn—while ionizing radiation penetrates deeper, damaging cells and their DNA. Within the ionizing spectrum, the depth of injury varies dramatically by particle type. Beta particles, unable to penetrate far, create shallow surface burns that closely resemble sunburn. Alpha particles, blocked by the keratin layer of the epidermis, cause only mild external reddening but can inflict severe internal damage if inhaled or ingested. Gamma radiation, depending on photon energy, can produce deep internal burns, with cobalt-60 being a common source. Even non-ionizing sources like cavity magnetrons and high-power radio transmitters can generate surface and internal thermal burns when the body absorbs and converts radio frequency energy into heat.
The Clinical Landscape of Radiation Dermatitis
Radiation dermatitis, or radiodermatitis, is the skin's visible response to ionizing radiation exposure, and it affects a strikingly high proportion of cancer patients. As many as 95 percent of individuals undergoing radiation therapy will experience some degree of skin reaction, whether or not chemotherapy is also administered. The condition manifests in three recognized forms. Acute radiodermatitis appears within weeks of starting treatment, presenting as red patches that may progress to peeling or blistering; visible erythema typically emerges within 24 hours of receiving an erythema dose, with redness appearing at doses of two grays or greater. Chronic radiodermatitis develops after prolonged exposure to sub-erythema doses, producing atrophic, indurated plaques that appear whitish or yellowish, often accompanied by telangiectasia and sometimes hyperkeratosis. A third, rarer form—an eosinophilic, polymorphic, and pruritic eruption—occurs most frequently in women receiving cobalt radiotherapy for internal cancers. In radiation ports, the condition can present as intense erythema with vesiculation of the skin.
Occupational Hazards and Medical Exposure Scenarios
Radiation burns extend well beyond accidental exposure, appearing in clinical and occupational settings where radiation is used deliberately. In interventional fluoroscopy, the high skin doses generated during procedures can trigger early skin reactions—within two months—or late reactions appearing months later, with necrosis in some cases. Historically, radiologists and radiographers bore the brunt of chronic radiation injury, particularly before the adoption of X-ray filters that reduced unnecessary exposure. In the broadcast and telecommunications world, the U.S. Federal Communications Commission sets 50 watts as the threshold above which radio stations must evaluate emission safety. Certain frequencies pose particular danger because the human body can become resonant, with 35 MHz, 70 MHz, the 80-to-100 MHz band, 400 MHz, and 1 GHz identified as especially hazardous. Microwave exposure at excessive intensity can likewise produce burns. Cavity magnetrons, when improperly used, present a risk of both surface and internal thermal injury, illustrating that even common household appliances carry potential for radiation-related harm when misapplied.
Delayed Reactions and the Long Shadow of Radiation
The consequences of radiation exposure do not always end when the acute phase resolves. Radiation recall reactions can surface months or even years after treatment, triggered by the subsequent administration of a chemotherapeutic agent; the previously irradiated area re-inflames with features mirroring the original dermatitis. Notably, no minimum dose threshold or established dose-response relationship has been identified for this phenomenon. Radiation acne, another delayed cutaneous condition, presents as comedo-like papules at sites of prior therapeutic exposure, emerging as the acute dermatitis phase begins to heal. Chronic radiodermatitis carries the most serious long-term risk: squamous cell and basal cell carcinomas may develop months to years after the initial exposure. This cancer risk underpins why radiation burns are routinely discussed alongside radiation-induced malignancy—ionizing radiation's capacity to damage DNA can occasionally push a cell toward uncontrolled growth. The latent period for chronic effects can stretch from several months to several decades, making the full clinical picture of a radiation injury a story that often unfolds over a lifetime.
Gallery





Frequently Asked Questions
What is a burn center?
A burn center is a specialized hospital department focused entirely on managing and recovering patients who have sustained serious burn injuries. It goes beyond general emergency care by providing targeted, long-term treatment for severe burns.
What other names is a burn center known by?
You'll also hear it referred to as a burn ward, burn unit, or burns unit depending on the region or institution. All of these terms point to the same dedicated facility for treating burn trauma.
Who makes up the medical team at a burn center?
The multidisciplinary team typically includes an intensivist, burn nurses, a plastic surgeon, a chest physician, a general surgeon, an anesthesiologist, a respiratory therapist, a pediatrician, various technicians, a microbiologist, a psychiatrist, a nutritionist, and a physiotherapist. This breadth of expertise ensures every aspect of a burn patient's recovery is covered.
Which patients are most likely to be referred to a burn center?
Infants, toddlers, and adults over 65 are at higher risk, particularly when burns involve the face, head, respiratory tract, chest, abdomen, groin, or limbs. Patients outside those age brackets may also be referred if they were already dealing with a pre-existing illness at the time of injury.
Why does a burn center matter in the healthcare system?
Severe burn injuries demand a level of specialized, coordinated care that a standard hospital ward simply cannot provide. A burn center consolidates every necessary specialty under one roof so that complex cases receive continuous, expert management from the moment of admission through full rehabilitation.
More in Burns 1-24
Spotted an error? Know more?
Reader corrections go straight into our review queue. Suggest an edit · How this site is sourced