
Allergic rhinitis
Allergic rhinitis is a common nasal inflammation from immune overreaction.

https://www.myupchar.com/en · CC BY-SA 4.0
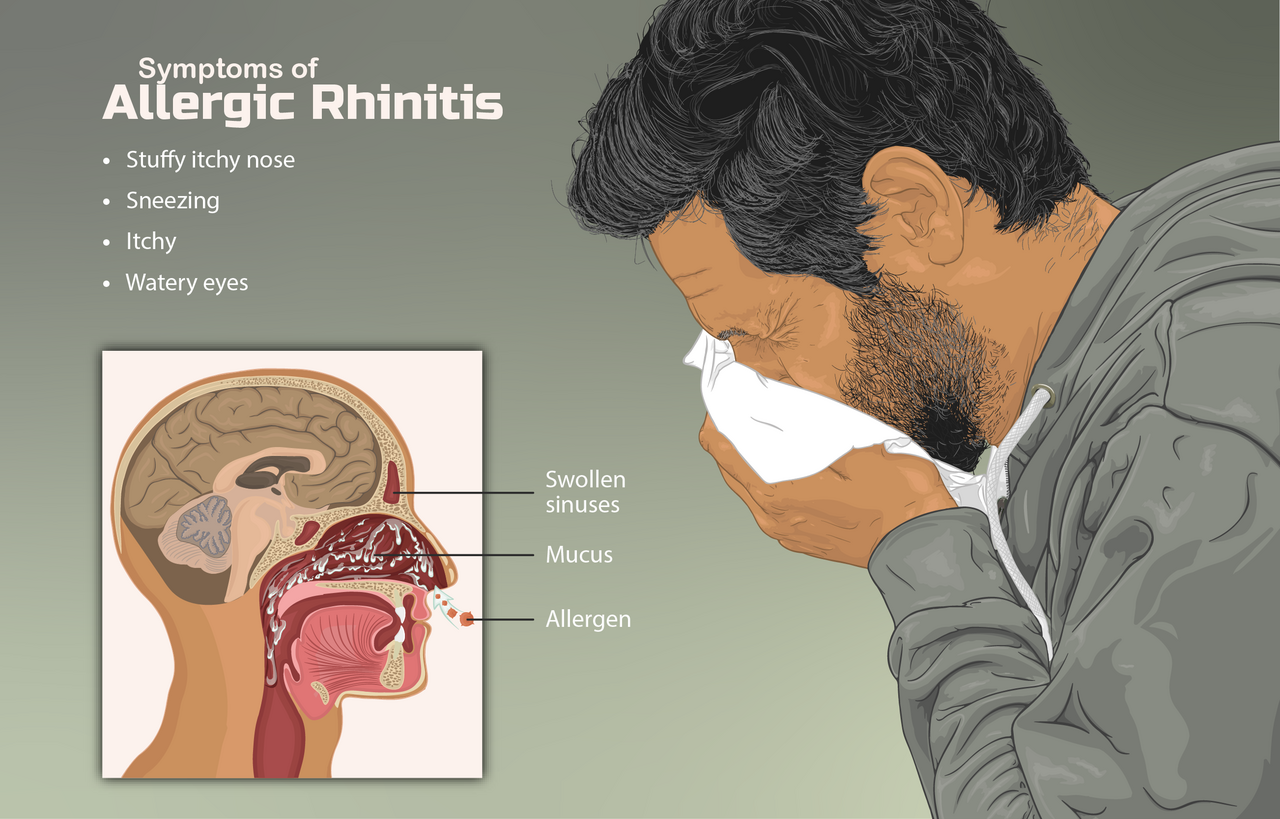
Allergic rhinitis, commonly known as hay fever when it occurs seasonally, is an inflammatory condition of the nose triggered by an overreaction of the immune system to airborne allergens. This reaction is classified as a type I hypersensitivity. Symptoms typically appear within minutes of exposure and include a runny or stuffy nose, sneezing, red and itchy eyes, watery eyes, and swelling around the eyes; the nasal discharge is generally clear. These symptoms can interfere with sleep, work, and study. For some people, symptoms are limited to certain times of the year, often due to pollen. Many individuals with this condition also have asthma, allergic conjunctivitis, or atopic dermatitis.
Common triggers include environmental allergens like pollen, pet dander, dust mites, and mold. A person’s genetic makeup and environmental exposures both play a role in developing allergies. Growing up on a farm or having several older siblings appears to lower the risk. The underlying process involves IgE antibodies binding to the allergen, which then triggers mast cells to release inflammatory chemicals such as histamine. This causes the mucous membranes in the nose, eyes, and throat to become inflamed and itchy as they try to expel the allergen. Diagnosis is usually based on symptoms combined with a skin prick test or blood test for allergen-specific IgE antibodies, though these tests can produce false positives. While allergy symptoms resemble those of the common cold, they typically last longer than two weeks and, despite the name, do not include a fever.
Early exposure to animals may reduce the risk of developing these allergies. Several medications can help, including nasal steroids, intranasal antihistamines (such as olopatadine or azelastine), second-generation oral antihistamines (like loratadine, desloratadine, cetirizine, or fexofenadine), the mast cell stabilizer cromolyn sodium, and leukotriene receptor antagonists (such as montelukast). However, medications often fail to fully control symptoms and may cause side effects. When first-line treatments are insufficient, allergen immunotherapy—exposing the person to gradually larger amounts of the allergen—is often effective. This can be given as an injection under the skin or as a tablet under the tongue, and treatment usually lasts three to five years, with benefits that may persist afterward.
- First accurate description
- 1819 by John Bostock
- Pollen identified as cause
- 1873 by Charles Blackley
Lore & Background
Allergic rhinitis is the type of allergy that affects the greatest number of people. In Western countries, between 10 and 30% of people are affected in a given year. It is most common between the ages of twenty and forty. The first accurate description is from the English physician John Bostock in 1819. In 1873, Charles Blackley definitively proved that pollen causes hay fever. In 1906, Clemens von Pirquet introduced the term 'allergy', though the specific mechanism of type I hypersensitivity (IgE-mediated) was not determined until later, notably by Kimishige Ishizaka and colleagues in the 1960s. The link with hay came about due to an early (and incorrect) theory that the symptoms were brought about by the smell of new hay.
Reader's Guide
Allergic rhinitis is typically triggered by environmental allergens such as pollen, pet hair, dust mites, or mold. Inherited genetics and environmental exposures contribute to the development of allergies. Growing up on a farm and having multiple older siblings are associated with a reduction of this risk. The underlying mechanism involves IgE antibodies that attach to an allergen, and subsequently result in the release of inflammatory chemicals such as histamine from mast cells. It causes mucous membranes in the nose, eyes and throat to become inflamed and itchy as they work to eject the allergen. Diagnosis is typically based on a combination of symptoms and a skin prick test or blood tests for allergen-specific IgE antibodies. These tests, however, can give false positives. The symptoms of allergies resemble those of the common cold; however, they often last for more than two weeks and, despite the common name, typically do not include a fever. Several different types of medications reduce allergic symptoms, including nasal steroids, intranasal antihistamines, 2nd generation oral antihistamines, the mast cell stabilizer cromolyn sodium, and leukotriene receptor antagonists. Exposing people to larger and larger amounts of allergen, known as allergen immunotherapy, is often effective and is used when first line treatments fail to control symptoms. Treatment typically lasts three to five years, after which benefits may be prolonged.
The Immune Misfire: How the Body Fights a Phantom Enemy
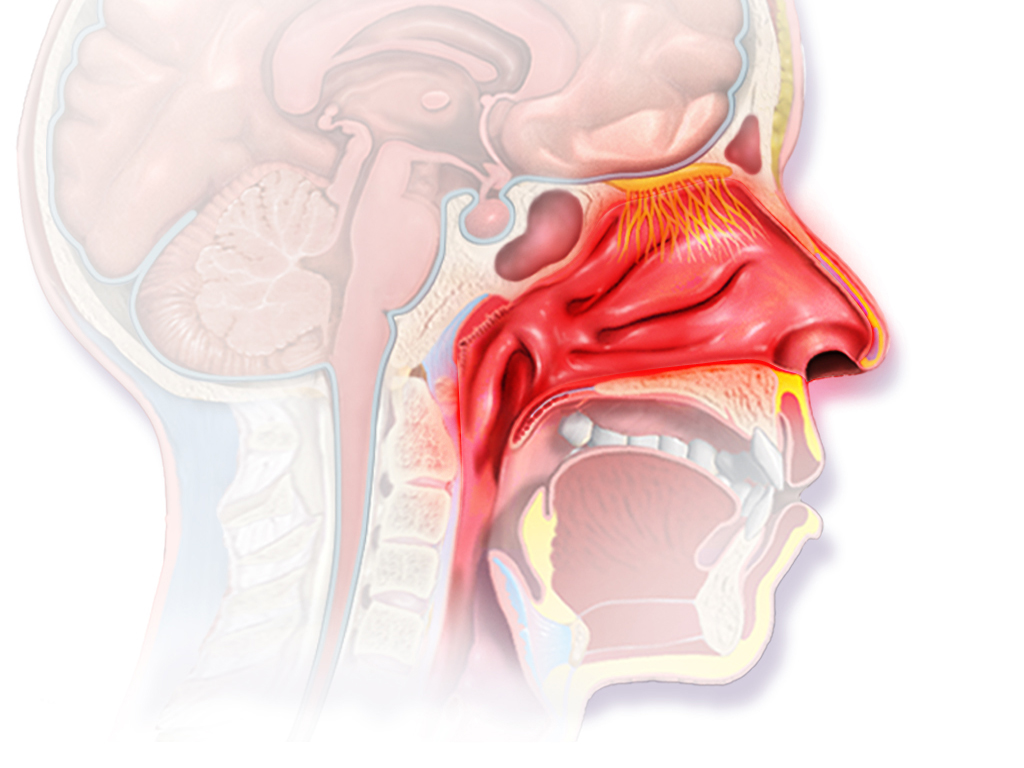
Allergic rhinitis is classified as a type I hypersensitivity reaction, meaning the body's defense machinery launches an exaggerated assault against harmless airborne substances. The process begins when IgE antibodies latch onto a specific allergen—pollen, pet dander, dust-mite proteins, or mold spores. This binding triggers mast cells to dump inflammatory chemicals, most notably histamine, into surrounding tissue. The result is inflammation of the mucous membranes lining the nose, eyes, and throat, as those tissues attempt to flush the perceived invader out. Symptoms typically appear within minutes of exposure and can include a runny or blocked nose, bouts of sneezing, red and watery eyes, and swelling around the eyelids. The nasal discharge is characteristically clear rather than the thick, colored mucus of an infection. Because the reaction can disrupt sleep and concentration, it significantly impairs a person's ability to work or study. The condition is the most widespread form of allergy, affecting roughly 10 to 30 percent of people in Western nations in any given year, with the highest prevalence between ages twenty and forty.
The Telltale Signs: Recognizing the Condition Beyond the Nose
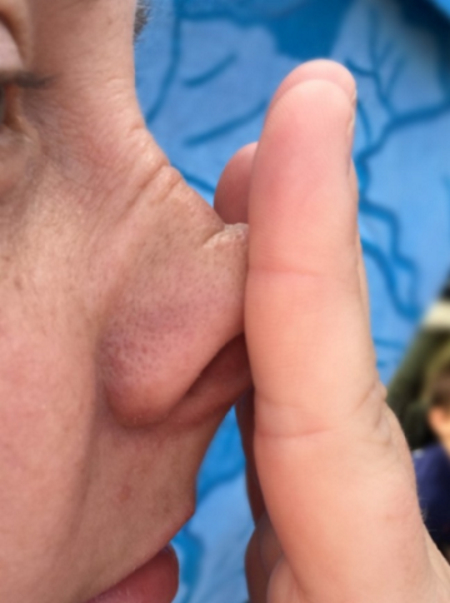
Beyond the classic runny nose and sneezing fits, allergic rhinitis leaves a distinctive physical signature. Conjunctival swelling and redness, puffy eyelids with Dennie–Morgan folds, and dark rings beneath the eyes—sometimes called allergic shiners—are common findings. Nasal endoscopy can reveal pale, swollen turbinates, stringy mucus coating the nasal passages, and a cobblestone-like texture of the mucosa. A particularly recognizable behavioral tell is the allergic salute: the habitual upward wipe of the nose with the palm to relieve irritation or mucus flow. Repeated over time, this gesture can press a horizontal crease across the bridge of the nose, known as the transverse nasal crease, and in extreme cases may cause permanent structural change. Cross-reactivity adds another layer: someone sensitive to birch pollen, for instance, may experience a scratchy throat after biting into an apple or sneeze while peeling a potato, because the proteins in those foods closely resemble the pollen allergen. Importantly, despite the name hay fever, the condition never raises core body temperature into the fever range of 37.5 to 38.3 °C, and symptoms typically persist well beyond the two-week window of a common cold.
From Farm to Pharmacy: Shaping Risk and Managing Symptoms
The risk of developing allergic rhinitis is shaped by both genetics and early-life environment. Children raised on farms and those with several older siblings appear to have a lower likelihood of becoming sensitized, and early exposure to animals may similarly reduce the chance of developing specific allergies. Conversely, air pollution and maternal tobacco smoking during pregnancy are associated with increased risk. Once the condition takes hold, a range of pharmacological options exists: intranasal corticosteroids, nasal antihistamines like olopatadine or azelastine, second-generation oral antihistamines including loratadine, cetirizine, and fexofenadine, the mast-cell stabilizer cromolyn sodium, and leukotriene receptor antagonists such as montelukast. Yet these drugs often fail to eliminate symptoms entirely and can carry side effects. For patients who remain uncontrolled, allergen immunotherapy—gradually introducing escalating doses of the triggering substance via subcutaneous injection or sublingual tablet—offers a longer-term strategy. A typical course spans three to five years, after which the protective benefit can persist. Diagnosis itself relies on symptom history combined with skin-prick testing or blood assays for allergen-specific IgE, though both methods can produce false-positive results.
A Thousand-Year Story: From Al-Razi to Modern Aerobiology
The earliest precise written account of what we now call allergic rhinitis comes from the 10th-century Persian physician Abu Bakr al-Razi, who described the characteristic nasal and ocular complaints. For centuries the true trigger remained a mystery. In 1859, Charles Blackley demonstrated that pollen, not the scent of freshly cut hay, was the actual culprit—despite the condition's enduring colloquial name hay fever, which persists from that early and incorrect theory. In 1906, Clemens von Pirquet identified the underlying immunological mechanism, laying groundwork for modern allergy science. Today the condition is the single most prevalent allergy worldwide. In Western countries, an estimated 10 to 30 percent of the population experiences it in a given year, with peak incidence between the ages of twenty and forty. It frequently co-occurs with asthma and atopic dermatitis, a cluster clinicians refer to as the atopic triad. The seasonal variety is driven primarily by the minute, wind-borne pollen grains of trees such as birch, cedar, and olive, while insect-pollinated plant grains are too large to stay airborne and therefore pose no risk. The study of how these bioaerosols travel through the atmosphere is known as aerobiology.
Gallery

Frequently Asked Questions
Who is Allergic rhinitis?
Allergic rhinitis is a type I hypersensitivity reaction in which the immune system overreacts to harmless airborne particles, inflaming the nasal passages. It is the condition most people know as hay fever when it flares up during pollen seasons.
What are Allergic rhinitis's powers/role?
Within minutes of allergen contact it unleashes sneezing, a runny nose with clear discharge, itchy red eyes, and swelling around the eyes. These effects can knock a person out of sleep, work, or study for the duration of the episode.
Why is Allergic rhinitis important?
It sits at the heart of allergy and immunology as one of the most widespread inflammatory conditions affecting the nose. Its seasonal peaks and day-to-day quality-of-life impact keep it a major focus of both clinical care and research.
What's Allergic rhinitis's origin story?
The 10th-century physician Abu Bakr al-Razi provided the first accurate description of the condition. Pollen was later singled out as a key trigger by Charles Blackley in 1859, and Clemens von Pirquet nailed down the immune mechanism in 1906.
More in Steroid-responsive inflammatory conditions 1-24
Spotted an error? Know more?
Reader corrections go straight into our review queue. Suggest an edit · How this site is sourced