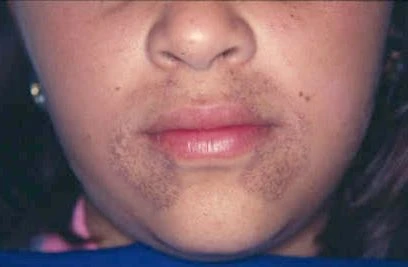
Citrullinemia
A urea cycle disorder causing toxic ammonia buildup.
Last updated
Citrullinemia is an autosomal recessive urea cycle disorder that leads to the accumulation of ammonia and other toxic substances in the blood. It results from errors in metabolism that disrupt the liver's ability to convert ammonia into urea for excretion. Two forms of citrullinemia exist, caused by mutations in different genes and presenting with distinct signs, symptoms, and management approaches.
Quick Facts
- Field
- Medical genetics
Facts from the source article.
Type I
Type I citrullinemia, also called classic citrullinemia, typically appears in the first days of life. Infants seem normal at birth but soon develop lethargy, poor feeding, vomiting, seizures, and loss of consciousness as ammonia accumulates; these problems can be life-threatening.
A milder form occasionally emerges in childhood or adulthood, and some individuals with causative gene mutations never show symptoms. Diagnosis involves elevated blood citrulline. This form, the most common, affects about one in 57,000 births worldwide and results from mutations in the ASS gene, which reduces argininosuccinate synthetase activity and disrupts the urea cycle.
Adolescent and adult citrin deficiency (formerly Type II citrullinemia)
Adolescent and adult citrin deficiency (AACD), previously termed type II citrullinemia, is a clinical phenotype of citrin deficiency caused by SLC25A13 gene mutations. Citrin, a mitochondrial transporter expressed in the liver, exchanges aspartate for cytosolic glutamate and a proton and participates in the malate-aspartate shuttle. Its dysfunction disrupts the urea cycle, glycolysis, gluconeogenesis, the TCA cycle, beta-oxidation, and de novo lipogenesis.
AACD manifests in adolescence or adulthood as the most severe form, featuring a strong preference for protein- and fat-rich foods, aversion to carbohydrates and sweets, hyperlipidemia, fatty liver, and hyperammonemia leading to neurological symptoms such as confusion, abnormal behavior, aggression, irritability, hyperactivity, seizures, and coma. Diagnosis involves elevated blood ammonia and citrulline, raised liver markers, characteristic food preferences, and genetic testing for SLC25A13 mutations.
Triggers include certain medications, serious infections, and high intake of carbohydrates, sugar, or alcohol. AACD occurs in an estimated one in 100,000 to 230,000 individuals, while citrin deficiency incidence in Japan is one in 17,000, indicating not all patients develop this phenotype.
Treatment
Treatment methods vary by type. For type I citrullinemia, low-protein diets minimize ammonia production, while arginine, sodium benzoate, and sodium phenylacetate help remove ammonia from the blood; dialysis may be used at critical levels. Liver transplant has been successful in some cases.
AACD dietary management differs markedly, recommending high-protein, high-fat, low-carbohydrate diets and medium-chain triglyceride oil supplementation, which improves symptoms. Intravenous high-concentration glucose or glycerol solutions should be avoided as they can worsen the condition and may be fatal; mannitol infusions are reported safe. Ammonia scavengers and L-arginine may be prescribed to manage ammonia levels.
More in Skin Conditions Resulting from Errors in Metabolism
Sources
Compiled from Wikipedia and the sources listed below. Text from Wikipedia is available under CC BY-SA 4.0; this entry is adapted from it.
- Wikipedia: Citrullinemia (CC BY-SA 4.0).
- Word definitions: the , each quoted from its Wikipedia article.
Spotted an error? Know more?
Reader corrections go straight into our review queue. Suggest an edit · How this site is sourced