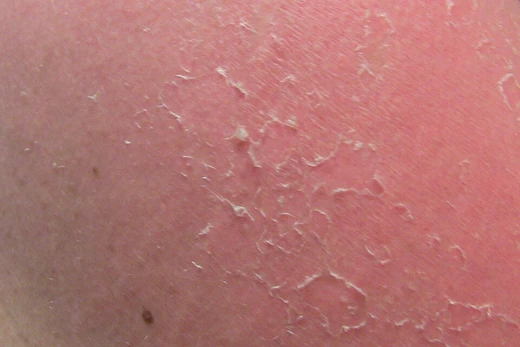
Desquamation
The shedding of dead skin cells from the outermost layer.

Barbariandeagle · CC0
Desquamation, commonly known as peeling skin, refers to the natural shedding of dead cells from the skin’s outermost layer. The word comes from the Latin *desquamare*, meaning “to scrape the scales off a fish.”
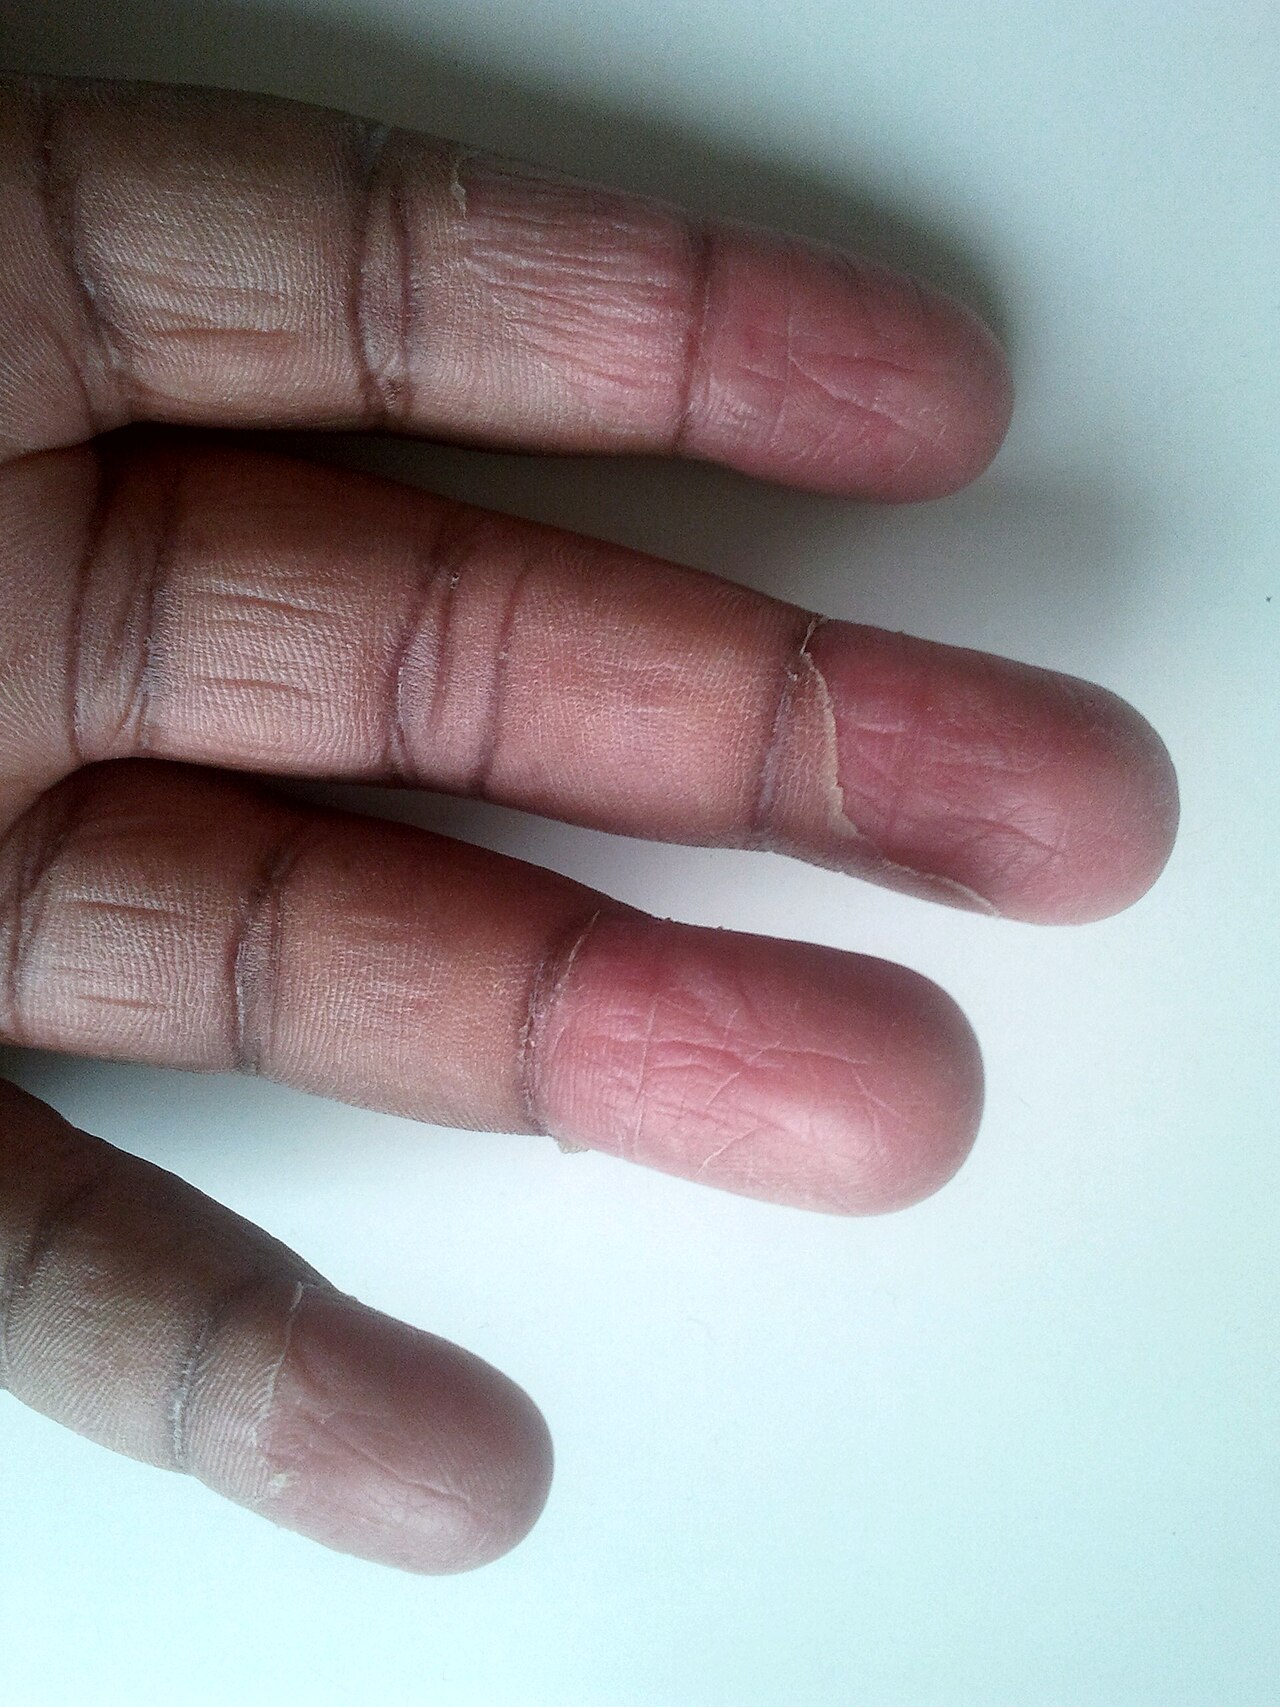
In healthy skin, this process is physiological and usually goes unnoticed. The epidermis, the skin’s outer layer, is made mostly of keratinocytes. These living cells are found in the basal, spinous, and granular layers. The topmost layer, the stratum corneum, consists of fully matured keratinocytes called corneocytes. In normal desquamation, individual corneocytes are shed invisibly from the skin’s surface. It typically takes about 14 weeks for a corneocyte to form and then be shed, though this timing varies by body location. For instance, desquamation is slower on the palms and soles (acral surfaces) and faster on thin skin like the eyelids. Normal shedding can be made visible by soaking skin in warm or hot water, which causes the outermost corneocytes to peel off—as happens after a hot bath or shower.
Corneocytes are held together by structures called corneodesmosomes. For desquamation to occur, these connections must be broken down. Keratinocytes in the stratum granulosum produce enzymes called kallikreins (especially KLK1, KLK5, and KLK7) that degrade corneodesmosomes. These serine proteases are packaged in lamellar bodies and released into the space between cells as keratinocytes turn into corneocytes. To prevent premature shedding, the same granular layer cells also produce proteins that inhibit kallikreins. On acral surfaces, desquamation is slower because these keratinocytes reduce production of KLK1 and KLK7 while increasing protease inhibitors, including the KLK5-specific SPINK9 and the cysteine protease inhibitors CSTA and CST3. This slowdown helps build a thick, protective stratum corneum on the palms and soles.
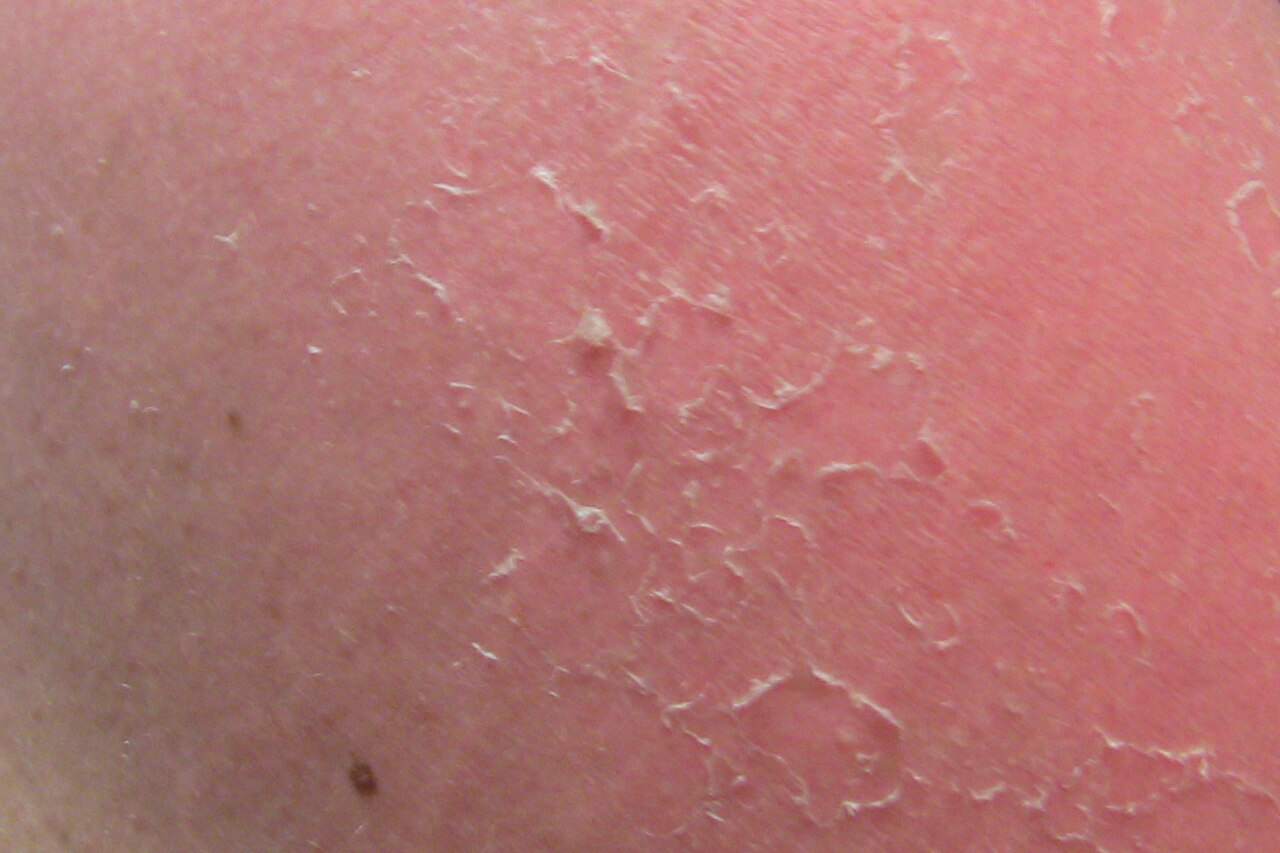
Abnormal desquamation leads to visible scale on the skin. In diseases like X-linked ichthyosis, the stratum corneum thickens (hyperkeratosis), giving the skin a dry, scaly look. Instead of shedding as single cells, corneocytes come off in clusters, forming visible flakes. Desquamation can also result from skin injury or illness. For example, the rash of measles is followed by peeling, and healing first-degree burns or sunburns often cause skin to peel.
Quick Facts
- Field
- Dermatology
Facts from the source article.
Lore & Background
In physiologic desquamation, keratinocytes in the epidermis differentiate into corneocytes in the stratum corneum. These corneocytes are held together by corneodesmosomes, which must be degraded for shedding to occur. Kallikrein family members (KLK1, KLK5, KLK7) produced by granular layer keratinocytes degrade these connections, while inhibitory proteins prevent premature desquamation. The process takes about 14 weeks on average, but varies by location—slower on palms and soles, faster on thin skin like eyelids. Normal desquamation can be visualized after immersion in warm or hot water.
Reader's Guide
Desquamation is significant as both a normal physiological process and a marker of disease. In health, it maintains the skin barrier by shedding individual corneocytes unnoticeably. In disease, abnormal desquamation leads to visible scale formation, as seen in X-linked ichthyosis, psoriasis, and atopic dermatitis. Pathologic desquamation can also result from burns, infections like toxic shock syndrome, or radiation. Understanding the molecular mechanisms—such as kallikrein regulation and protease inhibitors—has implications for diagnosing and treating skin disorders. Lipid composition changes in scale have been used to construct diagnostic models for human skin disease. The process also affects eye tissues like the conjunctiva and cornea in conditions such as dry eye syndrome.
Did You Know?
- Normal desquamation takes about 14 weeks from corneocyte formation to shedding.
- Desquamation occurs more slowly on palms and soles and more rapidly on eyelids.
- Toxic shock syndrome and mercury poisoning can cause severe desquamation.
The Natural Shedding Cycle
The outermost layer of human skin, known as the stratum corneum, is built entirely from corneocytes—keratinocytes that have reached their final, terminally differentiated state. These cells originate deeper in the epidermis, where living keratinocytes occupy the basal, spinous, and granular layers before maturing upward. Under healthy conditions, each corneocyte is released from the skin's surface as a single, invisible unit, a process so gradual that most people never notice it happening. The full journey from a newly formed corneocyte to its eventual shedding typically spans around fourteen weeks, though this timeline shifts depending on where the skin sits on the body. Palms and soles, where the stratum corneum is thick and protective, turn over more slowly, while the delicate skin of the eyelids sheds its cells at a noticeably faster pace. One simple way to make this quiet process visible is to soak the skin in warm or hot water, as during a bath or shower, which loosens the outermost corneocytes and causes them to flake away in small, observable sheets.
The Molecular Machinery of Shedding
Corneocytes do not simply fall away on their own; they are held together by specialized junctions called corneodesmosomes, and desquamation cannot begin until these connections are chemically broken down. The enzymes responsible belong to the kallikrein family—specifically KLK1, KLK5, and KLK7—all of which are serine proteases produced by keratinocytes in the granular layer. These enzymes are packaged inside lamellar bodies and then released into the intercellular space as the keratinocytes complete their transition into corneocytes. To keep the process from running ahead of schedule, the same granular-layer cells also manufacture kallikrein-inhibitory proteins that act as molecular brakes. At acral sites such as the palms and soles, this braking system is amplified: the cells reduce their output of KLK1 and KLK7 while simultaneously increasing production of the KLK5-specific inhibitor SPINK9 and the cysteine protease inhibitors CSTA and CST3. This deliberate slowdown allows the stratum corneum in those regions to build up into a thick, durable shield that withstands the constant friction of gripping and walking.
When Shedding Turns Pathological
Under disease or injury, the orderly single-cell shedding of healthy skin breaks down, and corneocytes are expelled in clusters that form visible scales on the surface. In X-linked ichthyosis, for instance, the stratum corneum thickens—a condition called hyperkeratosis—giving the skin a persistently dry, scaly look. Desquamation also follows the fading of a measles rash, the healing of a first-degree burn or sunburn, and the severe immune reactions seen in toxic shock syndrome triggered by Staphylococcus aureus. Mercury poisoning, Stevens–Johnson syndrome, and toxic epidermal necrolysis can all produce extreme peeling, while radiation therapy may cause either dry or moist desquamation. Chronic immune-mediated conditions such as psoriasis and atopic dermatitis likewise disturb the normal shedding rhythm. Researchers have exploited the altered lipid composition found within these pathological scales to build diagnostic models that help identify and classify human skin diseases, turning the body's own waste product into a source of clinical information.
Etymology and Desquamation Beyond the Skin
The very word "desquamation" carries a vivid image from the ancient world: it derives from the Latin desquamare, meaning to scrape the scales off a fish. That aquatic metaphor aptly captures the layered, flaky nature of the process. While desquamation is most familiar as a skin phenomenon, it is not limited to the epidermis. Certain tissues of the eye, including the conjunctiva and the cornea, can undergo pathological desquamation, a feature observed in conditions such as dry eye syndrome. The lens, however, is anatomically exempt; its internal structure makes the shedding of surface cells physically impossible. The broader family of related conditions extends well beyond the skin and eyes: desquamative gingivitis affects the gums, pityriasis describes flaking of the skin, and spalling refers to the peeling of surfaces in other biological and material contexts. Together, these terms illustrate that the fundamental principle of a surface layer detaching in sheets or flakes is a recurring theme across many tissues and disciplines.
Gallery




Frequently Asked Questions
Who is Desquamation?
Desquamation is the physiological process by which the body sheds dead keratinocytes from the stratum corneum, the outermost layer of the epidermis. The term derives from the Latin word desquamare, which literally means to scrape scales off a fish.
What is Desquamation's role in the body?
In healthy skin, individual corneocytes—fully matured keratinocytes—detach one by one from the stratum corneum in a process so gradual that it typically goes completely unnoticed. This continuous turnover keeps the outer skin layer thin and functional.
What happens when Desquamation goes wrong?
When shedding becomes excessive or disordered, it manifests as visible peeling or flaking, a hallmark sign in conditions like psoriasis, atopic dermatitis, and X-linked ichthyosis. Severe systemic triggers such as toxic shock syndrome or Stevens–Johnson syndrome can also produce dramatic desquamation.
Why is Desquamation important to dermatology?
It serves as a key clinical sign that helps clinicians identify underlying skin and systemic disorders. Abnormal patterns of shedding—whether too rapid, too slow, or patchy—can point toward specific diagnoses within the field.
Who are Desquamation's most notable associates?
The conditions most commonly linked to abnormal desquamation include X-linked ichthyosis, psoriasis, atopic dermatitis, toxic shock syndrome, and Stevens–Johnson syndrome. Each presents with a distinct pattern of skin shedding that aids in differential diagnosis.
More in Symptoms and signs: Skin and subcutaneous tissue 1-23
Spotted an error? Know more?
Reader corrections go straight into our review queue. Suggest an edit · How this site is sourced