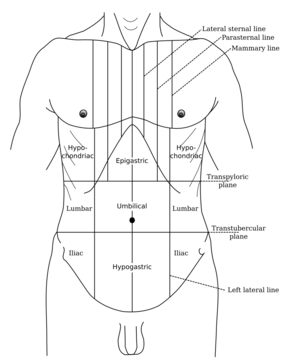
Abdominal guarding
Involuntary abdominal muscle spasm indicating internal inflammation.

U.S. Navy photo by Mass Communication Specialist 2nd Class Greg Mitchell · Public domain
Abdominal guarding is a clinical sign characterized by the involuntary tensing of the abdominal wall muscles to protect inflamed internal organs from pressure-induced pain. It is a key finding in the physical examination of patients with an acute abdomen, often indicating peritoneal inflammation from conditions such as appendicitis or diverticulitis. Also known as 'défense musculaire', guarding is detected when the abdominal wall is pressed, and the muscle spasm occurs automatically to shield tender underlying tissues.
- Field
- Medicine (Physical Examination Sign)
- Known for
- Involuntary abdominal muscle tensing indicating peritoneal inflammation
- Associated conditions
- Appendicitis, Diverticulitis, Peritonitis
- Diagnostic method
- Abdominal wall palpation
Lore & Background
Abdominal guarding is a reflexive tensing of the abdominal wall muscles that occurs when inflamed organs within the abdomen are pressed upon. This spasm is detected during physical examination and serves as a protective mechanism to keep tender underlying tissues from being disturbed. The sign is commonly associated with acute abdominal conditions such as appendicitis and diverticulitis, where peritoneal inflammation is present.
Reader's Guide
Abdominal guarding is a critical clinical sign in the evaluation of acute abdominal pain, as it points to underlying peritoneal irritation. Its presence helps narrow the differential diagnosis to conditions like appendicitis, diverticulitis, perforated peptic ulcer, or pelvic inflammatory disease. The sign is distinct from voluntary guarding, as it is an involuntary reflex. In practice, guarding prompts further diagnostic workup including laboratory tests (e.g., complete blood count, amylase/lipase) and imaging such as CT or ultrasound to identify the specific cause. Prompt recognition of guarding can lead to early intervention, including surgery for life-threatening emergencies like hemorrhage or sepsis. The sign's reliability and simplicity make it a cornerstone of the abdominal examination.
Did You Know?
- Abdominal guarding is also known as 'défense musculaire'.
- It is detected when the abdominal wall is pressed during physical examination.
- The tensed muscles automatically go into spasm to keep tender underlying tissues from being disturbed.
- Guarding is a characteristic finding in an acute abdomen with peritoneal inflammation.
The Physiological Reflex and Its Naming
Abdominal guarding is a protective muscular response in which the muscles of the abdominal wall contract and tense in order to shield inflamed internal organs from the pain that would result from external pressure. This reflexive tightening is identified during a physical examination when a clinician presses against the abdominal wall and encounters unexpected resistance. The phenomenon is also referred to by its French medical term, défense musculaire, a label that underscores the defensive nature of the muscle contraction. The underlying mechanism is straightforward: when tissues deep within the abdomen become tender—whether from infection, trauma, or other inflammatory processes—the overlying musculature goes into involuntary spasm. This automatic response serves a clear biological purpose, preventing the already-sensitive underlying structures from being further disturbed by movement or palpation. Rather than being a conscious choice made by the patient, the tensing is an involuntary protective reflex that signals to the examining physician that something beneath the muscle layer is in a state of acute irritation or inflammation.
A Hallmark Sign of the Acute Abdomen
In clinical practice, abdominal guarding stands out as one of the most telling findings when a physician examines a patient presenting with a suddenly painful abdomen, a presentation commonly termed the acute abdomen. The sign becomes particularly significant when the peritoneal surface—the inner lining of the abdominal cavity—has become inflamed. Conditions such as appendicitis and diverticulitis are classic examples in which peritoneal irritation triggers the abdominal wall muscles to lock into spasm, effectively creating a muscular barrier between the examiner's fingers and the tender, inflamed tissue below. The reflex is not a deliberate act of the patient; it is an automatic, involuntary contraction that the body initiates to minimize further mechanical disturbance of the affected area. Because the tensing is detected specifically when the abdominal wall is pressed, it provides the clinician with a tangible, reproducible indicator that the pathology lies beneath the muscle layer rather than in the skin or subcutaneous tissue. Recognizing this sign early can prompt the urgent diagnostic workup that an acute abdomen demands, potentially accelerating the identification of surgical emergencies and the initiation of life-saving intervention.
The Broad Differential Landscape
One of the most important aspects of abdominal guarding is the extraordinary breadth of conditions it can accompany, making it a sign that demands thorough investigation rather than immediate assumption. The differential diagnosis spans surgical emergencies such as perforated peptic ulcer disease, mesenteric ischemia, incarcerated hernia, and bowel obstruction, as well as gynecological urgencies including ectopic pregnancy, ovarian cysts, pelvic inflammatory disease, and septic miscarriage. Vascular catastrophes like abdominal aortic aneurysm and hepatic or splenic laceration also feature prominently. Beyond these acute threats, the list extends to infectious causes such as spontaneous bacterial peritonitis, pyelonephritis, and zoster—whose characteristic skin lesions may not appear until a day or two after the initial symptoms. Other considerations include nephrolithiasis, pancreatitis, intussusception, inflammatory bowel disease, blunt abdominal trauma, and even non-organic explanations such as malingering, anxiety, or abdominal migraine. Insect toxins, notably from the black widow spider, and abdominal wall strain round out a differential that underscores why guarding, while informative, is never diagnostic on its own.
From Laboratory Workup to Definitive Treatment
Once guarding is identified, the diagnostic pathway is multi-layered. Blood work typically includes a complete blood count, blood urea nitrogen and creatinine, liver function tests, glucose, amylase and lipase levels, electrolytes, and urinalysis with urine culture. In women of reproductive age, a beta-hCG test and cervical cultures for pelvic inflammatory disease are essential. Imaging plays a critical role: CT scans can reveal organ contusion, laceration, aneurysm, diverticulitis, and appendicitis, while pelvic, abdominal, or transvaginal ultrasound can identify peritonitis, ectopic pregnancy, ovarian cysts, free fluid or blood from trauma, and aneurysm. A KUB x-ray may detect nephrolithiasis or abnormal bowel gas patterns. Additional tools include paracentesis for suspected spontaneous bacterial peritonitis, gastrointestinal endoscopy for peptic ulcer disease, and H. pylori testing. Treatment is condition-specific but often begins with hemodynamic stabilization, volume replacement, and broad-spectrum antibiotics if perforation or intra-abdominal infection is suspected. Nasogastric decompression may be needed for obstruction with persistent vomiting, while early sepsis or active hemorrhage can escalate the situation to a life-threatening surgical emergency.
Gallery

Frequently Asked Questions
Who is Abdominal guarding?
Abdominal guarding is an involuntary reflex in which the muscles of the abdominal wall tense up to shield irritated or inflamed internal organs from further pressure. It is a recognized clinical sign encountered during physical examination, also referred to by its French name, défense musculaire.
What are Abdominal guarding's powers/role?
Its primary role is to serve as an automatic protective spasm that prevents additional pain to tender underlying tissues when the abdomen is pressed. Clinically, it signals that the peritoneum is inflamed, pointing toward conditions like appendicitis, diverticulitis, or peritonitis.
Why is Abdominal guarding important?
It is a critical finding in the assessment of an acute abdomen because it helps clinicians distinguish peritoneal inflammation from other causes of abdominal pain. Its presence narrows the differential diagnosis and often accelerates the decision to pursue urgent intervention.
How do fans (clinicians) detect Abdominal guarding?
The sign is elicited through careful abdominal wall palpation, where the examiner presses into the abdomen and notes the automatic, non-volitional muscle spasm. Unlike voluntary rigidity, guarding occurs reflexively and cannot be consciously suppressed by the patient.
More in Symptoms and signs: Digestive system and abdomen 1-24
Spotted an error? Know more?
Reader corrections go straight into our review queue. Suggest an edit · How this site is sourced