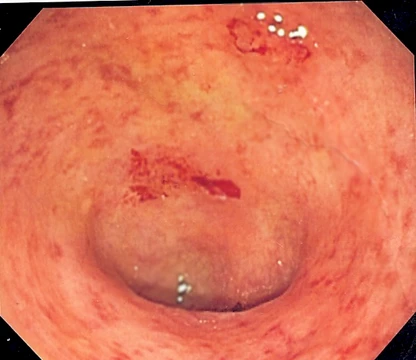
Duodenal lymphocytosis
A condition of increased intra-epithelial lymphocytes in the duodenum, often linked to coeliac disease but with many possible causes.
Last updated
Duodenal lymphocytosis, also referred to as lymphocytic duodenitis, lymphocytic duodenosis, or duodenal intraepithelial lymphocytosis, is diagnosed when a microscopic examination of duodenal tissue reveals an abnormally high count of intra-epithelial lymphocytes. While this finding is frequently linked to coeliac disease, it can also occur in other conditions.
Presentation
On microscopic analysis, the condition is defined by a lymphocyte proportion exceeding 20–25 per 100 enterocytes within the duodenal epithelium. Intra-epithelial lymphocytes (IELs) are normally present in the intestine, with higher counts in the crypts and jejunum, and are distinct from lymphocytes in the lamina propria. Most IELs are T cells. Elevated IEL numbers appear in roughly 3% of duodenal biopsies, though this figure can reach up to 7% depending on the patient population studied.
Causes
A broad range of conditions can cause duodenal lymphocytosis, including coeliac disease, environmental enteropathy (tropical sprue), autoimmune enteropathy, small intestinal bacterial overgrowth, damage from NSAIDs, Helicobacter pylori infection, other infections, and Crohn’s disease.
Diagnosis
Diagnosis relies on precise counting of intra-epithelial lymphocytes during histological examination. A key requirement is that the rest of the duodenal tissue appears normal, particularly with intact villous architecture. In coeliac disease, this finding represents the mildest stage of histological change, known as Marsh I, and is seen in untreated or partially treated cases. More advanced stages involve villous atrophy and crypt hyperplasia.
About 11% of duodenal lymphocytosis cases show coeliac disease–related antibodies—IgA endomysial and anti-transglutaminase antibodies—which are highly sensitive and specific for coeliac disease, indicating that this subset definitely has the condition. Roughly 33% of cases carry the HLA-DQ2 allele, present in over 90% of people with coeliac disease.
The absence of HLA-DQ2 (or the rarer HLA-DQ8) makes coeliac disease very unlikely. Since antibody-negative coeliac disease exists, HLA status, persistence or progression of IEL counts after a gluten challenge, and symptom improvement on a gluten-free diet have been used to confirm the diagnosis. In one series of over 200 adults, this approach identified coeliac disease in 22% of cases.
Helicobacter pylori infection is commonly found during endoscopy, and while duodenal IEL counts are slightly higher with this infection, it is not considered a meaningful cause in children. Other infections, such as cryptosporidiosis and giardiasis, can also raise IEL numbers.
Management
Management targets any identified underlying disorder—for example, a gluten-free diet for coeliac disease or treatment for associated infections.
When duodenal lymphocytosis occurs alongside other coeliac disease features—particularly positive antibodies, HLA-DQ2/8, or a family history—a gluten-free diet reduces IEL counts. In one study, 23 of 85 patients developed gluten sensitivity or coeliac disease over two years; predictors included diarrhoea, thyroiditis, weakness, and folate deficiency.
Microscopic Identity and Prevalence
Duodenal lymphocytosis—also referred to in the literature as lymphocytic duodenitis, lymphocytic duodenosis, or duodenal intraepithelial lymphocytosis—describes a histological finding rather than a single disease entity. When a pathologist examines a duodenal mucosal biopsy under the microscope, the hallmark is an elevated density of intra-epithelial lymphocytes (IELs) residing within the epithelial layer of the duodenum. The conventional threshold for calling this abnormal sits at roughly 20 to 25 IELs per 100 enterocytes.
These lymphocytes, predominantly T cells, are a normal resident population of the intestinal epithelium, with baseline numbers tending to be higher in the crypt regions and in the jejunum compared with the duodenum. They are anatomically and functionally distinct from the lymphocytes that populate the lamina propria beneath the epithelium. In routine practice, an IEL count above the threshold is encountered in approximately three percent of duodenal biopsies, though some series report figures climbing toward seven percent, suggesting the finding may be increasingly recognized as case mixes shift and counting techniques refine.
A Broad Differential: Beyond Coeliac Disease
Although duodenal lymphocytosis is most frequently discussed in the context of coeliac disease, the underlying aetiology is far from singular. The differential spans a wide spectrum of conditions. Tropical sprue and other forms of environmental enteropathy can provoke the same epithelial lymphocyte infiltration. Autoimmune enteropathy, small intestinal bacterial overgrowth, and mucosal injury from non-steroidal anti-inflammatory drugs all feature on the list.
Infectious agents play a notable role: Helicobacter pylori colonisation, Cryptosporidiosis, and Giardiasis have each been linked to elevated IEL counts. Crohn's disease, when it involves the duodenum, may also present with this histological pattern. In paediatric populations, Helicobacter infection is a common endoscopic finding, and while IEL counts tend to be marginally higher in its presence, clinicians have generally not regarded it as a meaningful driver of the lymphocytosis in children.
The breadth of this differential underscores that an elevated IEL count is a shared histological response to diverse mucosal insults rather than a pathognomonic marker of any one disease.
Treatment Pathways and Long-Term Outlook
Because duodenal lymphocytosis is a histological descriptor rather than a standalone disease, management is directed at whatever underlying condition is identified. In cases where coeliac disease is confirmed, a strict gluten-free diet remains the cornerstone of therapy, and this intervention has been shown to reduce IEL numbers over time. When an infection such as Helicobacter pylori, Cryptosporidium, or Giardia is the culprit, targeted antimicrobial or antiparasitic treatment addresses the root cause.
NSAID-related mucosal injury, by contrast, calls for withdrawal or substitution of the offending agent. The long-term prognosis hinges on whether the lymphocytosis is an isolated finding or a harbinger of evolving gluten sensitivity. In one prospective series of eighty-five patients, twenty-three progressed to overt coeliac disease within two years. Several clinical and serological features flagged those at higher risk: positive coeliac antibodies, the presence of HLA-DQ2 or HLA-DQ8, a family history of the condition, and accompanying symptoms such as chronic diarrhoea, thyroiditis, unexplained weakness, and folate deficiency.
Recognising these predictors allows clinicians to monitor more closely and intervene early, potentially preventing the full histological and nutritional consequences of established coeliac disease.
More in Inflammatory diseases of the digestive system
Sources
Compiled from Wikipedia and the sources listed below. Text from Wikipedia is available under CC BY-SA 4.0; this entry is adapted from it.
- Wikipedia: Duodenal lymphocytosis (CC BY-SA 4.0).
- Word definitions: the , each quoted from its Wikipedia article.
Spotted an error? Know more?
Reader corrections go straight into our review queue. Suggest an edit · How this site is sourced