
Amiodarone induced thyrotoxicosis
Hyperthyroidism caused by the antiarrhythmic drug amiodarone.

Vaccinationist · Public domain
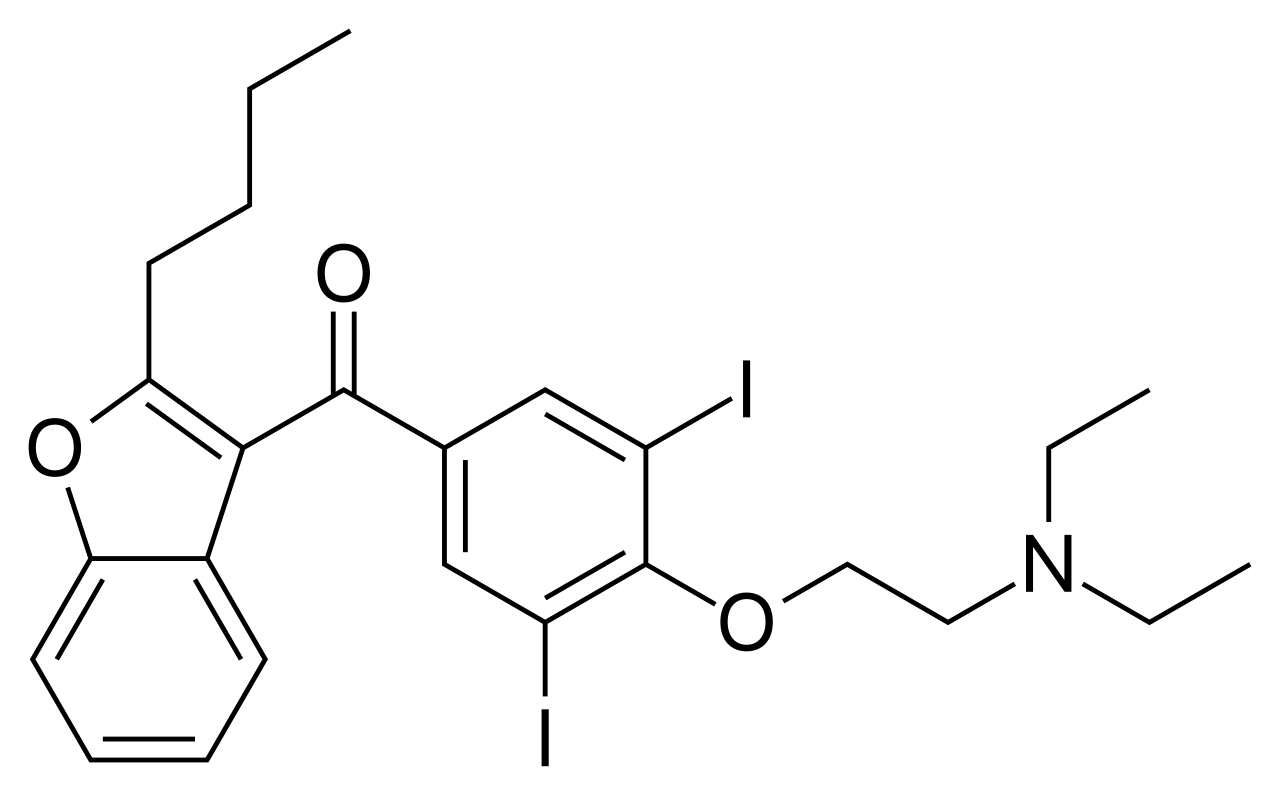
Amiodarone-induced thyrotoxicosis (AIT) is a condition where the thyroid becomes overactive as a side effect of the antiarrhythmic drug amiodarone. While the drug more often causes an underactive thyroid—affecting 6 to 32 percent of users—overactivity is rarer, occurring in 1 to 12 percent of patients. The rate of AIT varies by location; it is more frequent in regions with low dietary iodine, where it appears in 10 to 12 percent of those on the drug. In the United States, clinical cases are seen in about 3 to 5 percent of patients.
Symptoms can start soon after beginning amiodarone or may not surface for years. They resemble those of other hyperthyroid conditions and include new or returning arrhythmias, worsening of existing heart problems like ischemic heart disease or heart failure, unexplained weight loss, and fever. Developing AIT raises the risk of major adverse cardiovascular events and increases mortality, especially in those who also have heart failure.
The drug affects the thyroid in several ways. Amiodarone is about one-third iodine by weight, so taking it can raise free iodine levels in the blood up to 40 times higher than typical dietary intake. Excess iodine can lead to overproduction of thyroid hormone. Normally, the thyroid protects itself through the Wolff-Chaikoff effect, which halts hormone production within a day or two. But in some cases, the gland escapes this mechanism via the Jod-Basedow phenomenon, resulting in hyperthyroidism instead. This phenomenon is a key contributor to AIT. Additionally, amiodarone acts as a thyroid hormone analog, interfering with enzymes involved in hormone production, and it directly damages thyroid tissue through cytotoxicity.
AIT often shows up late, with studies noting an average delay of about two years. The drug’s long half-life—due to its lipid solubility and tissue distribution—means it clears slowly from the body, prolonging toxicity. Pre-existing heart conditions like dilated cardiomyopathy and cardiac sarcoidosis are considered predictive factors for developing AIT.
There are three subtypes. Type 1 arises from the Jod-Basedow phenomenon: the iodine in amiodarone is used by the thyroid to make excess hormones. This mainly affects people with pre-existing thyroid issues, such as nodular goiter or latent Graves’ disease, where thyroid tissue has lost its normal regulation.
Quick Facts
- Specialty
- Endocrinology
Facts from the source article.
Lore & Background
Amiodarone induced thyrotoxicosis (AIT) arises from both direct and indirect effects of amiodarone on thyroid function. The drug is approximately one-third iodine by weight, elevating free circulating iodine levels up to 40 times the average American dietary intake. This excess iodine can trigger the Jod-Basedow phenomenon, where the thyroid escapes the normal Wolff-Chaikoff effect and overproduces thyroid hormone. Additionally, amiodarone acts as a thyroid hormone analog, affects enzymes in thyroid hormone production, and causes direct cytotoxicity and damage to thyroid tissues.
Reader's Guide
AIT is classified into subtypes based on pathophysiology. Type 1 results from the Jod-Basedow phenomenon in patients with pre-existing thyroid disease (e.g., nodular goiter or latent Graves' disease) and typically appears within weeks to months of starting amiodarone. Type 2 is a destructive thyroiditis due to an immune response to amiodarone's cytotoxic effects, occurring in patients with a normal thyroid gland and potentially appearing years after initiation. Mixed/indefinite AIT (type 3) is used when classification is unclear. Diagnosis involves thyroid hormone levels, radionucleotide scans, thyroid ultrasonography with color-flow-Doppler, and interleukin-6 or beta-glucoronidase levels, though no single gold standard exists. Treatment differs by subtype: type 1 uses thionamides and sodium perchlorate, with possible radioiodine or thyroidectomy; type 2 is treated with glucocorticoids; type 3 combines both modalities. Persistent cases may require plasmapheresis or surgery. Regular thyroid monitoring is recommended during amiodarone treatment and for at least one year after cessation.
Did You Know?
- AIT type 1 primarily occurs in patients with pre-existing thyroid disease such as nodular goiter or latent autoimmune Graves' disease.
- AIT type 2 is a form of destructive thyroiditis caused by an immune response to amiodarone's cytotoxic properties.
- The average delayed presentation of AIT is 2 years after starting amiodarone.
The Liver as a Chemical Processing Hub and Its Inherent Vulnerability
The liver serves as the body's primary chemical processing center, responsible for transforming and clearing a vast array of substances it encounters. This very function makes it uniquely susceptible to damage from the agents it handles. The term hepatotoxin describes any chemical capable of injuring this organ, and the list of offenders is extensive: more than 900 drugs alone have been linked to liver injury. Beyond pharmaceuticals, the threat extends to laboratory and industrial chemicals, natural toxins such as alpha-amanitin, and even herbal remedies like kava and comfrey. A critical clinical challenge is that many of these chemicals cause subclinical damage, meaning the liver is being harmed but the only visible sign is an abnormality in liver enzyme blood tests. Drug-induced liver injury is far from a rare curiosity; it accounts for roughly five percent of all hospital admissions and half of all acute liver failure cases, making it one of the most consequential causes of liver disease in modern medicine.
Two Fundamentally Different Pathways of Drug-Induced Liver Injury
Adverse drug reactions that injure the liver fall into two fundamentally different categories. Type A, or intrinsic, hepatotoxicity represents roughly 80 percent of all toxic drug reactions and follows a predictable dose-response relationship: the higher the concentration, the greater the damage. These agents have well-characterized mechanisms, either directly destroying liver tissue or disrupting a metabolic pathway, and injury typically appears once a toxicity threshold is crossed. Carbon tetrachloride is a classic example used in animal research to model this acute, dose-dependent injury. In stark contrast, type B, or idiosyncratic, injury strikes without warning in susceptible individuals, bears no relationship to dose, and carries a variable latency period. Because no clear temporal or dose-response pattern exists, predictive models are largely unavailable. This unpredictability is precisely why drugs like troglitazone and trovafloxacin were pulled from the market after passing rigorous FDA clinical trials, and why the herb kava has produced liver injuries ranging from asymptomatic enzyme elevations to fatal outcomes.
Paracetamol Overdose and the Lethal NAPQI Cascade
Paracetamol, marketed under names like Tylenol and Panadol, is generally well tolerated at prescribed doses, yet overdose with this single compound remains the leading cause of drug-induced liver disease and acute liver failure worldwide. The mechanism is elegant in its lethality: cytochrome P-450 enzymes in the liver convert paracetamol into a toxic metabolite called N-acetyl-p-benzoquinone imine, or NAPQI. Under normal conditions, phase 2 conjugation with glutathione neutralizes this compound. In overdose, however, the volume of NAPQI generated overwhelms the detoxification capacity and liver cells are destroyed, with nitric oxide contributing to the toxic cascade. Several factors modulate the risk, including the ingested dose, concurrent alcohol or other drug use, and the time gap between ingestion and antidote administration. Chronic alcoholics appear particularly vulnerable, with a lower toxic threshold. The life-saving intervention is acetylcysteine, a glutathione precursor that captures free NAPQI. Patients who progress to acute liver failure may recover spontaneously, but those showing encephalopathy or coagulopathy, assessed via King's College Criteria, may require transplantation.
A Wider Spectrum of Hepatotoxic Agents and the Demand for Early Detection
The hepatotoxic landscape extends well beyond paracetamol. NSAIDs, despite their enormous global use, have emerged as a significant hepatotoxic class, with both dose-dependent and idiosyncratic reactions documented across agents like ibuprofen, diclofenac, and piroxicam. Glucocorticoids, while primarily associated with hepatic steatosis during prolonged use, can rarely cause liver enlargement in children. Isoniazid, a cornerstone of tuberculosis therapy, produces mild enzyme elevations in up to 20 percent of patients and severe hepatotoxicity in one to two percent. Anti-thyroid drugs such as methimazole and propylthiouracil commonly raise liver enzymes, making baseline testing before treatment initiation essential for distinguishing drug injury from the underlying hyperthyroidism. The sheer scale of implicated compounds, over 900 drugs, drives urgent demand for toxicity prediction models and early-stage screening assays, including stem cell-derived hepatocyte-like cells, to catch liver toxicity before a drug ever reaches a patient.
Gallery
Frequently Asked Questions
Who is Amiodarone induced thyrotoxicosis?
AIT is a hyperthyroid complication that arises when the antiarrhythmic drug amiodarone pushes the thyroid gland into an overactive state. It is the less common thyroid side effect of the drug, sitting opposite the more frequent amiodarone-induced hypothyroidism.
What are Amiodarone induced thyrotoxicosis's powers/role?
It drives classic hyperthyroid symptoms by forcing excess thyroid hormone production or release. Onset is unpredictable: some patients notice signs within weeks of starting therapy, while others do not present until roughly two years later.
Why is Amiodarone induced thyrotoxicosis important?
It complicates care for a meaningful slice of patients—about 3–5 percent in iodine-sufficient settings like the United States—forcing clinicians to balance heart-rhythm control against thyroid toxicity. In iodine-deficient regions the incidence jumps to 10–12 percent, highlighting how background iodine status shapes drug–thyroid interactions.
Where does Amiodarone induced thyrotoxicosis appear most often?
The condition strikes hardest in geographies with low dietary iodine, where up to 12 percent of amiodarone users develop overt thyrotoxicosis. Iodine-replete populations see a lower but still notable 3–5 percent clinical rate.
More in Drug-induced diseases 1-20
Spotted an error? Know more?
Reader corrections go straight into our review queue. Suggest an edit · How this site is sourced