Frequently Asked Questions
The most-asked questions about symptoms and signs: digestive system and abdomen.
What does the phrase 'symptoms and signs of the digestive system and abdomen' actually cover?
It refers to any abnormal sensation a patient reports (symptom) or any observable finding a clinician detects (sign) arising from the esophagus, stomach, intestines, liver, gallbladder, pancreas, or surrounding structures. The scope ranges from mild, self-limiting discomfort to life-threatening emergencies.
What is the practical difference between a 'symptom' and a 'sign' in abdominal medicine?
A symptom is subjective—only the patient can report it, such as nausea, cramping, or bloating—whereas a sign is objective and detectable by an examiner, like jaundice, a palpable mass, or absent bowel sounds. Both categories together form the complete clinical picture used for diagnosis.
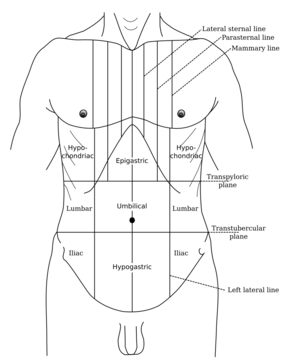
How do clinicians divide the abdomen to localise a complaint?
The standard approach splits the abdomen into four quadrants or nine regions, each associated with particular organs. For example, right-lower-quadrant tenderness classically implicates the appendix, while epigastric pain more often points to the stomach or duodenum.
Which digestive symptoms do patients most frequently report?
Abdominal pain or cramping, nausea, vomiting, diarrhoea, constipation, and bloating consistently top primary-care visit lists and large patient surveys. Together they account for the overwhelming majority of gastrointestinal complaints seen in everyday clinical practice.
What 'red-flag' findings should prompt urgent medical evaluation?
Sudden severe abdominal pain, persistent vomiting with inability to retain fluids, visible blood in vomit or stool, unexplained rapid weight loss, and new-onset jaundice are widely cited as warning signs that warrant same-day assessment. Delaying care when these appear can allow treatable conditions to progress.
What are the typical first steps a clinician takes when evaluating a new abdominal complaint?
The standard workup begins with a focused history—onset, character, triggers, and associated symptoms—followed by a structured abdominal exam (inspection, auscultation, percussion, palpation). Targeted laboratory tests or imaging are then ordered based on the emerging differential diagnosis.
How do the liver, gallbladder, and pancreas produce distinctive abdominal signs?
These accessory organs sit in the upper abdomen and, when inflamed or obstructed, generate characteristic patterns: right-upper-quadrant pain with jaundice for gallbladder disease, or central epigastric pain radiating to the back for pancreatitis. Recognising these patterns helps narrow the differential quickly.
Why do sources stress the distinction between 'functional' and 'organic' digestive symptoms?
Functional disorders such as irritable bowel syndrome produce real, measurable symptoms without identifiable structural damage on standard testing, whereas organic causes like ulcers or inflammatory bowel disease show clear anatomical or histological changes. Distinguishing the two fundamentally guides the treatment strategy.
What misconceptions do newcomers most often hold about abdominal symptoms?
Many assume any abdominal pain signals a serious disease, while others dismiss persistent changes in bowel habits as 'just stress.' In practice, most acute complaints are benign and self-limiting, but progressive or persistent changes do merit a proper diagnostic workup.
Where should a beginner start to build a solid understanding of this topic?
A general internal-medicine or gastroenterology textbook chapter on the gastrointestinal system, paired with a reputable plain-language patient-education resource covering basic anatomy and common conditions, provides the strongest foundation. From there, exploring individual disorders in depth becomes much more manageable.