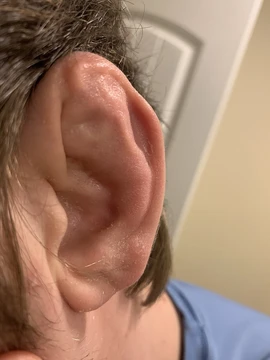
Ear pain
Pain in the ear, often from infection or referred sources.
Ear pain, also known as earache or otalgia, is pain felt in the ear. It can originate from the ear itself (primary ear pain) or be referred from another part of the body (secondary ear pain). Most causes are not life-threatening, and primary ear pain is more common than secondary ear pain.
Quick Facts
- Field
- ENT surgery
Facts from the source article.
Did You Know?
- Cerumen impaction occurs in 1 out of every 10 children, 1 in every 20 adults, and 1 in every 3 elderly citizens.
- Barotrauma occurs around 1 in every 1000 people.
- The otoscope was invented in the 1840s by Anton von Troeltsh in Germany.
Causes
Ear pain has many causes, most of which are not life-threatening. Primary ear pain originates from the ear itself, while secondary ear pain is referred from another anatomic structure. Primary ear pain is more common in children, whereas secondary pain is more common in adults. Primary ear pain is most often due to infection or injury to a part of the ear. Conditions of the external ear are often visible to the naked eye; the external ear is vulnerable to trauma or environmental exposures. Blunt trauma, such as a blow to the ear, can cause a hematoma between the cartilage and perichondrium, common in contact sports like wrestling and boxing. Environmental injuries include sunburn, frostbite, or contact dermatitis. Less common causes of external ear pain include auricular cellulitis, perichondritis, and relapsing polychondritis. Otitis externa, or swimmer's ear, is a cellulitis of the external ear canal; in North America, 98% of cases are bacterial, most commonly caused by Pseudomonas and Staph aureus. Risk factors include excessive moisture and disruption of the cerumen barrier from aggressive cleaning or placing objects in the ear.
Diagnostic
Most causes of ear pain are diagnosed clinically, without need for specific imaging. Because the differential is broad, there is no consensus on the best diagnostic framework. One approach differentiates by time course: primary causes are typically more acute, while secondary causes are more chronic. Acute causes may be distinguished by the presence or absence of fever. Chronic pain may be broken down by the presence of red flags. Red flags include smoking, heavy alcohol use (more than 3.5 drinks per day), diabetes, coronary artery disease, and age over 50. Secondhand smoke may increase risk of acute otitis media in children. Swimming is the most significant risk factor for otitis externa. If red flags are present, additional workup such as a CT scan or biopsy may be needed to rule out malignant otitis externa, mastoiditis, temporal arteritis, or cancer. The presence of a red flag does not guarantee a diagnosis, as any symptom can be seen in a variety of situations. If no red flags are present, other sources of referred ear pain become more likely.
Management
Management depends on the underlying cause. Bacterial infections are usually treated with antibiotics that cover common organisms for that infection. Many bacterial ear infections are treated with cleaning, topical or systemic antibiotics, and oral analgesics. Warm compresses may benefit some infections. Uncomplicated acute bacterial otitis externa is treated with topical or systemic antibiotics; if symptoms do not respond within 10 days, necrotizing external otitis should be considered. Acute otitis media self-resolves within 24–48 hours in 80% of cases; if not, systemic antibiotics are used, and if symptoms persist after a week, mastoiditis should be evaluated. Acute folliculitis, auricular cellulitis, suppurative otitis media, and perichondritis are also treated with antibiotics. Perichondritis requires evaluation by an otorhinolaryngologist; if a foreign body is present in the cartilage, it should be removed. Sinusitis causing secondary ear pain is treated by addressing the sinusitis. Necrotizing external otitis and acute mastoiditis require hospital admission, IV antibiotics, and otorhinolaryngology consultation. Some causes require procedural management, such as removal of impacted keratin debris in keratosis obturans, or surgical debridement for chronic perichondritis or chondritis.
Society and culture
There was a strong tradition of treating acute otitis media with amoxicillin, reflected in a quote from the 1980s that any child with an earache has an acute amoxicillin deficiency. Overuse of antibiotics can cause bacterial resistance, leading to antibiotic stewardship, a systematic effort to educate prescribers to give antibiotics only when warranted. Most ear pain in children resolves by itself without complications, and guidelines help determine when antibiotics are needed. The ear also played a role in acupuncture, known as auriculotherapy, believed to correct other pain or disorders in the body. Such practices may date back to the Stone Age. The first European documentation of auriculotherapy was in the 1600s, when a physician described stimulating the ear to treat sciatic pain, and another applied it for toothache. Paul Nogier is known as the father of ear acupuncture.
More in Diseases of the Ear and Mastoid Process
Spotted an error? Know more?
Reader corrections go straight into our review queue. Suggest an edit · How this site is sourced